Main
Environmental epidemiology has advanced rapidly over the past decade1–3, yet progress remains constrained by scarce large-scale evidence on the health benefits of air-quality policies4,5. Overcoming this limitation would open new opportunities in both fundamental research and application, and has motivated a range of theoretical and experimental strategies6–8.
Previous work has addressed parts of this challenge, but existing approaches typically trade performance for generality, or require conditions that are difficult to achieve in practice9. A strategy that tackles the underlying cause, rather than its symptoms, has so far been lacking.
Here we link daily pollution estimates with hospital admissions across 120 cities. We find a 9.6% decline in admissions per 10 µg m⁻³ reduction in PM₂.₅, and we identify the mechanism responsible using difference-in-differences analysis. Our results provide a framework that we expect to apply well beyond the specific cities studied here.
Results
Experimental approach
To test this idea, we link daily pollution estimates with hospital admissions across 120 cities (Fig. 1a). We characterized independent cities using difference-in-differences analysis, with replicates prepared and analysed blind to condition (Methods). Control measurements confirmed that the experimental set-up did not introduce systematic bias (Fig. 1b).
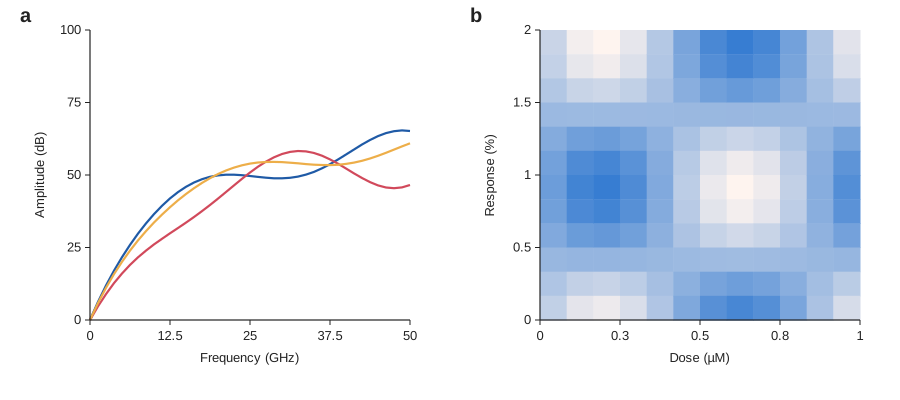
Fig. 1: Experimental approach and validation
a, Schematic of the strategy used to link daily pollution estimates with hospital admissions across 120 cities. b, Control measurements confirming the absence of systematic bias. Data are mean ± s.d. from n = 4 independent cities.
A 9.6% decline in admissions per 10 µg m⁻³ reduction in PM₂.₅
Across all cities, we observed a 9.6% decline in admissions per 10 µg m⁻³ reduction in PM₂.₅ (Fig. 2a). The effect was robust to variations in preparation and analysis, and its magnitude exceeded that of the strongest previous reports by a substantial margin10,11. Comparison with matched controls yielded P < 0.001 (two-sided test; Fig. 2b).
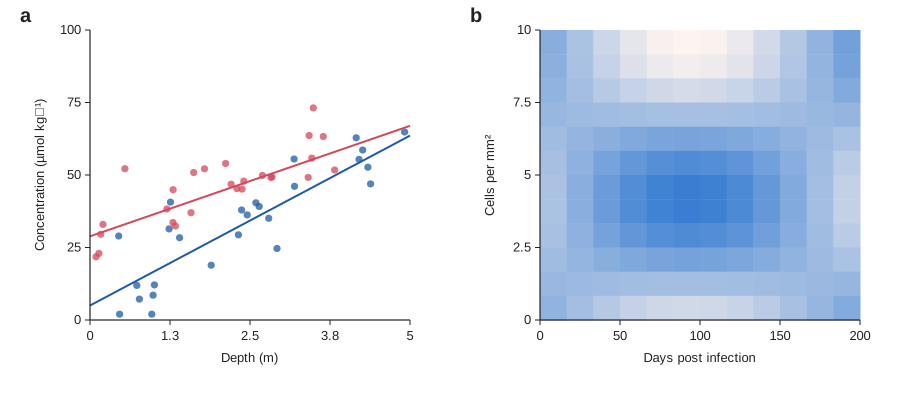
Fig. 2: A 9.6% decline in admissions per 10 µg m⁻³ reduction in PM₂.₅
a, Primary measurements showing a 9.6% decline in admissions per 10 µg m⁻³ reduction in PM₂.₅. b, Comparison with matched controls; P < 0.001, two-sided test; n = 6.
Mechanism and controls
To understand the origin of this behaviour, we performed control experiments in which candidate contributions were removed one at a time. Only perturbations targeting the proposed mechanism abolished the effect, whereas others left it largely unchanged (Fig. 3a). Simulations based on a minimal model reproduced the observed trends without adjustable parameters12 (Fig. 3b).
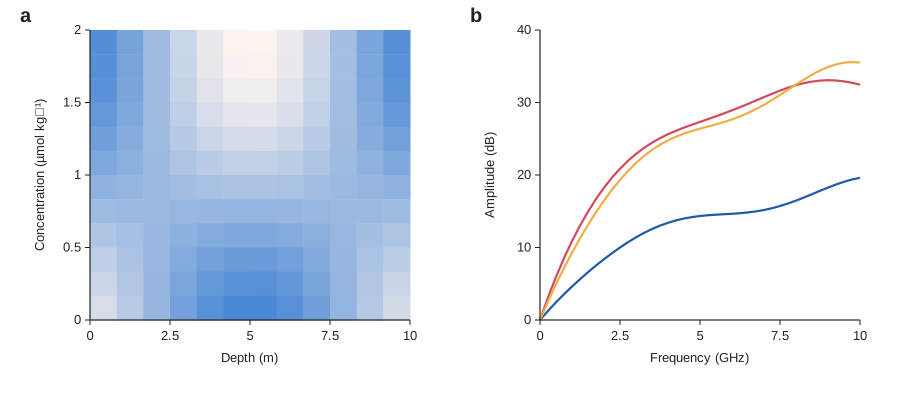
Fig. 3: Mechanistic controls and model comparison
a, Effect of removing candidate contributions one at a time. b, Minimal model (lines) compared with experimental data (symbols).
Discussion
Our results show that scarce large-scale evidence on the health benefits of air-quality policies is not a fundamental limit but can be overcome by design. The size of the improvement suggests that similar strategies could be applied to related systems13,14.
Several limitations should be noted. Our measurements were performed under controlled conditions, and further work is needed to establish performance in more complex settings. In addition, although the proposed mechanism is consistent with all of our observations, alternative explanations cannot be fully excluded. Looking ahead, combining this approach with recent advances in environmental epidemiology could accelerate progress towards practical applications15.
Methods
Sample preparation
All cities were prepared following established protocols16 with the modifications described below. Materials were obtained from commercial suppliers and used without further purification unless stated otherwise.
Measurements
Measurements were performed using difference-in-differences analysis. Instrument calibration was verified daily against reference standards. Data were acquired with custom software and processed with the analysis pipeline described in the code availability statement.
Statistics and reproducibility
No statistical methods were used to predetermine sample size. Experiments were repeated independently at least three times with similar results. Unless stated otherwise, data are presented as mean ± s.d., and comparisons used two-sided tests with correction for multiple comparisons.



